This post adheres to Policy and guidelines on the use of generative AI models in posts on Virological.org on the use of generative AI models.
This analysis reflects the Pathoplexus database state of 17 October 2026. Our previous post Reproduction number of the 2026 Bundibugyo virus disease outbreak over time: phylodynamic estimates from genomes collected up to 6 September 2026 described the phylodynamic estimates from genomes collected up to 6 September 2026.
Summary
- Using the phylodynamic program Delphy, we estimated the reproduction number of the 2026 Bundibugyo virus disease (BVD) outbreak over time from 838 Bundibugyo virus (BDBV) genomes collected from 2 May to 5 October 2026, 90 % of them from seven health zones of Ituri Province, including Bunia and Rwampara. We refer to this as the “primary analysis”.
- Before the outbreak was declared (1 March – 15 May 2026), the effective population size of the virus doubled every 14 days, and one case infected about two others on average: R = 1.94 (95 % highest posterior density interval (HPD) 1.57–2.31). This is similar to estimates for the 2007 BVD outbreak in Uganda [1] and the Ebola virus disease epidemic in West Africa [2]. The first genome was collected on 2 May, so this period is seen through the branching of lineages sampled later.
- After the official declaration, growth slowed within a month: R = 1.27 (1.00–1.56) for 15 May – 15 June 2026, and R = 0.86 (0.73–0.99) for 15 June – 27 September 2026. The median for this last period is below 1 in all analyses, but its 95 % HPD interval reaches or exceeds 1 in several of them (Figure 2), so R below 1 is not firmly established.
- Robustness. In 13 analyses with other BDBV genome subsets and Delphy settings, the median R before the official declaration lies between 1.76 and 2.11. A second phylodynamic program, BEAST X, gives nearly the same estimates with the same model apart from the two programs’ default priors (Methods). The model smooths changes of the population size over time, and the primary analysis fixes the strength of this smoothing; estimated from the genomes instead, it gives a higher and less precise estimate before the official declaration, 2.22 (1.55–3.00) with Delphy and 2.31 (1.56–3.47) with BEAST X, and later estimates of 1.20 and 0.92–0.93.
- Scope. The estimates describe the virus population sampled in Ituri. Reported cases in Nord-Kivu rose until mid-September, and only 10 genomes are recorded there, all in the analysed set. The results are preliminary.
Background
An outbreak of Bundibugyo virus disease in the Democratic Republic of the Congo (DRC) was declared on 15 May 2026 [3]. By 11 October 2026 (INSP situation report N°150), 9,0661 confirmed cases had been reported in the DRC, 6,695 of them in health zones of Ituri, 1,911 in those of Nord-Kivu, and 459 in other provinces.
1 The health-zone figures sum to 9,065; the situation reports show small differences from the national total.
Methods
- Claude Science. All analyses were performed with the assistance of Claude Science (Anthropic), which was used to run the phylodynamic analyses, estimate reproduction numbers, and generate figures and tables; all outputs were reviewed by the authors, and the code and parameter settings are available at GitHub - inrb-labgenpath/inrb_bdbv_claude_science · GitHub.
- Genomes. We downloaded all 1,014 BDBV genomes of the 2026 outbreak from Pathoplexus on 18 October 2026 (data version 1792278748 of 17 October), used its alignment to the reference NC_014373, and masked the last 40 positions because of sequencing artefacts there [3, 7]. We analysed 838 genomes (817 from the DRC, 20 from Uganda, 1 from a patient medically evacuated from the DRC to Germany). Of the other 176, 12 lacked a collection date precise to the day; 77 shared a sample identifier with another record (we kept the more complete record if the two genomes were identical, neither if they differed); 2 were restricted-use genomes whose submitters had not yet agreed to their use; and 85 failed quality checks of the consensus sequence, which flag genomes that carry no mutation although collected when such genomes had become rare, and genomes whose mutations contradict those of related genomes (estimates with these 85 included, 923 genomes: Figure 2). Genomes with signs of ADAR editing were kept: where a genome carried three or more T-to-C (or A-to-G) changes from the majority base, each within 300 nucleotides of the next, we kept the first and masked the others (set to N; 96 of the 838 genomes, 342 positions).
- Phylodynamic model. We used Delphy 1.4.1 [8] with the HKY substitution model, a strict molecular clock, and a Skygrid coalescent prior in the piecewise-constant form of [5], which BEAST X also uses (20 parameters, intervals of 15.4 days), and ran 24 chains of 1.5 × 10⁹ steps, discarding the first 30 % of each. The coalescent prior was evaluated on 8,000 cells in time instead of Delphy’s default of 400: with the default, 18 of 24 chains had to be discarded, 16 of them with the root of the tree next to the earliest genome; with 1,000 or 16,000 cells the medians change by at most 0.01 (Figure 2). Under the Skygrid prior the logarithm of the population size follows a random walk from one interval to the next. In intervals with many coalescences the estimate follows the genomes almost regardless of the precision of this walk; in intervals with few, the precision determines how far the estimate can depart from its neighbours and how wide its interval is. We call this precision the smoothing. The primary analysis fixes the smoothing at Delphy’s default (precision 4.06) rather than estimating it: a priori, the population size changes by a factor of 2 or less within 30 days with probability 68 %. This default reflects the developers’ judgement of what gives stable inference and plausible fluctuations [8], not information from these genomes, and we have no independent basis for choosing a value for this outbreak. To examine the effect of this choice, we also fixed the smoothing over 15 and 60 days (Figure 2) and, separately, estimated it from the genomes with both Delphy and BEAST X 10.5.0 [9] (BEAST X: Figure 1a; Results); for Delphy with the smoothing estimated, 9 of 16 chains were used, the others excluded by criteria fixed before the analyses. To look for changes over shorter times, we repeated the primary analysis with a finer grid of 32 parameters and intervals of 7.2 days (“weekly grid”; six chains; smoothing again at Delphy’s default, precision 8.64 for these intervals, i.e. the same prior on the change of the population size within 30 days; otherwise the settings of the primary analysis). Its estimates are the diamonds in Figure 1d and one row of Figure 2.
- Periods. We report three periods (Figure 1b): P1, 1 March – 15 May (before the outbreak was declared); P2, 15 May – 15 June (early outbreak response); and P3, 15 June – 27 September (established outbreak response). The choice was not blind to the data: we had already seen analyses of a large part of these genomes, including our previous post [7]. P3 is further divided at 1 August into 15 June – 1 August and 1 August – 1 September (the weeks after 1 September are too uncertain to report separately; Results); we mark these periods as exploratory, because a boundary chosen where a change was already visible can overstate that change.
- Reproduction number. For each period we first took the growth rate r of the effective population size, i.e. the change in ln Neτ between the first and last day of the period divided by its length in days (Neτ is the effective population size multiplied by the generation time of the coalescent model). We then converted r to R with R = (1 + r σ²/μ)^(μ²/σ²) [6], assuming a gamma-distributed generation time with mean μ = 15.3 days and standard deviation σ = 9.3 days, the serial interval of Ebola virus disease in West Africa [2], as none has been estimated for Bundibugyo virus disease (a limitation also noted in [1]). As a rough check against reported cases, we fitted a line to the logarithm of weekly confirmed cases, by date of report, in the seven health zones that supply 90 % of the genomes (Bunia, Rwampara, Nizi, Mongbwalu, Lita, Mangala, and Bambu) and converted its slope to R with the same formula.
- Comparison with BEAST X. We also analysed the data with BEAST X (eight chains of 40 million states, the first 30 % discarded), once with the model of the primary analysis and once with the smoothing estimated. By default, Delphy adds to the prior a penalty on values of Neτ below one day [8]; BEAST X has none, and the two programs’ default priors on the evolutionary rate differ.
- Analyses without recent genomes of Bunia. The primary analysis was repeated on four sets without 95 or all 148 of the Bunia genomes collected since 5 August, and on six control sets with as many recent genomes removed at random irrespective of place (six chains each; not shown in Figure 2).
Results
Before the official outbreak declaration. Between 1 March and 15 May, Neτ grew at 0.049 per day, a doubling time of 14 days and R = 1.94 (1.57–2.31) (Figure 1). Under the smoothing prior alone (what the model would give with no genomes), R for this period lies between 0.63 and 1.48 with 95 % probability; the estimate’s interval lies above this range, so it is informed by the genomes. The earliest genomes were collected on 2 and 3 May: 62 of the period’s 75 days precede sampling, so it is seen mainly through the branching of lineages sampled later.
After the official outbreak declaration. For 15 May – 15 June the estimate is R = 1.27 (1.00–1.56), slower growth than before the official declaration with posterior probability above 0.99; for 15 June – 27 September it is 0.86 (0.73–0.99), and an exploratory division of this period gives 0.95 (0.83–1.08) for 15 June – 1 August and 0.70 (0.54–0.88) for 1 August – 1 September.
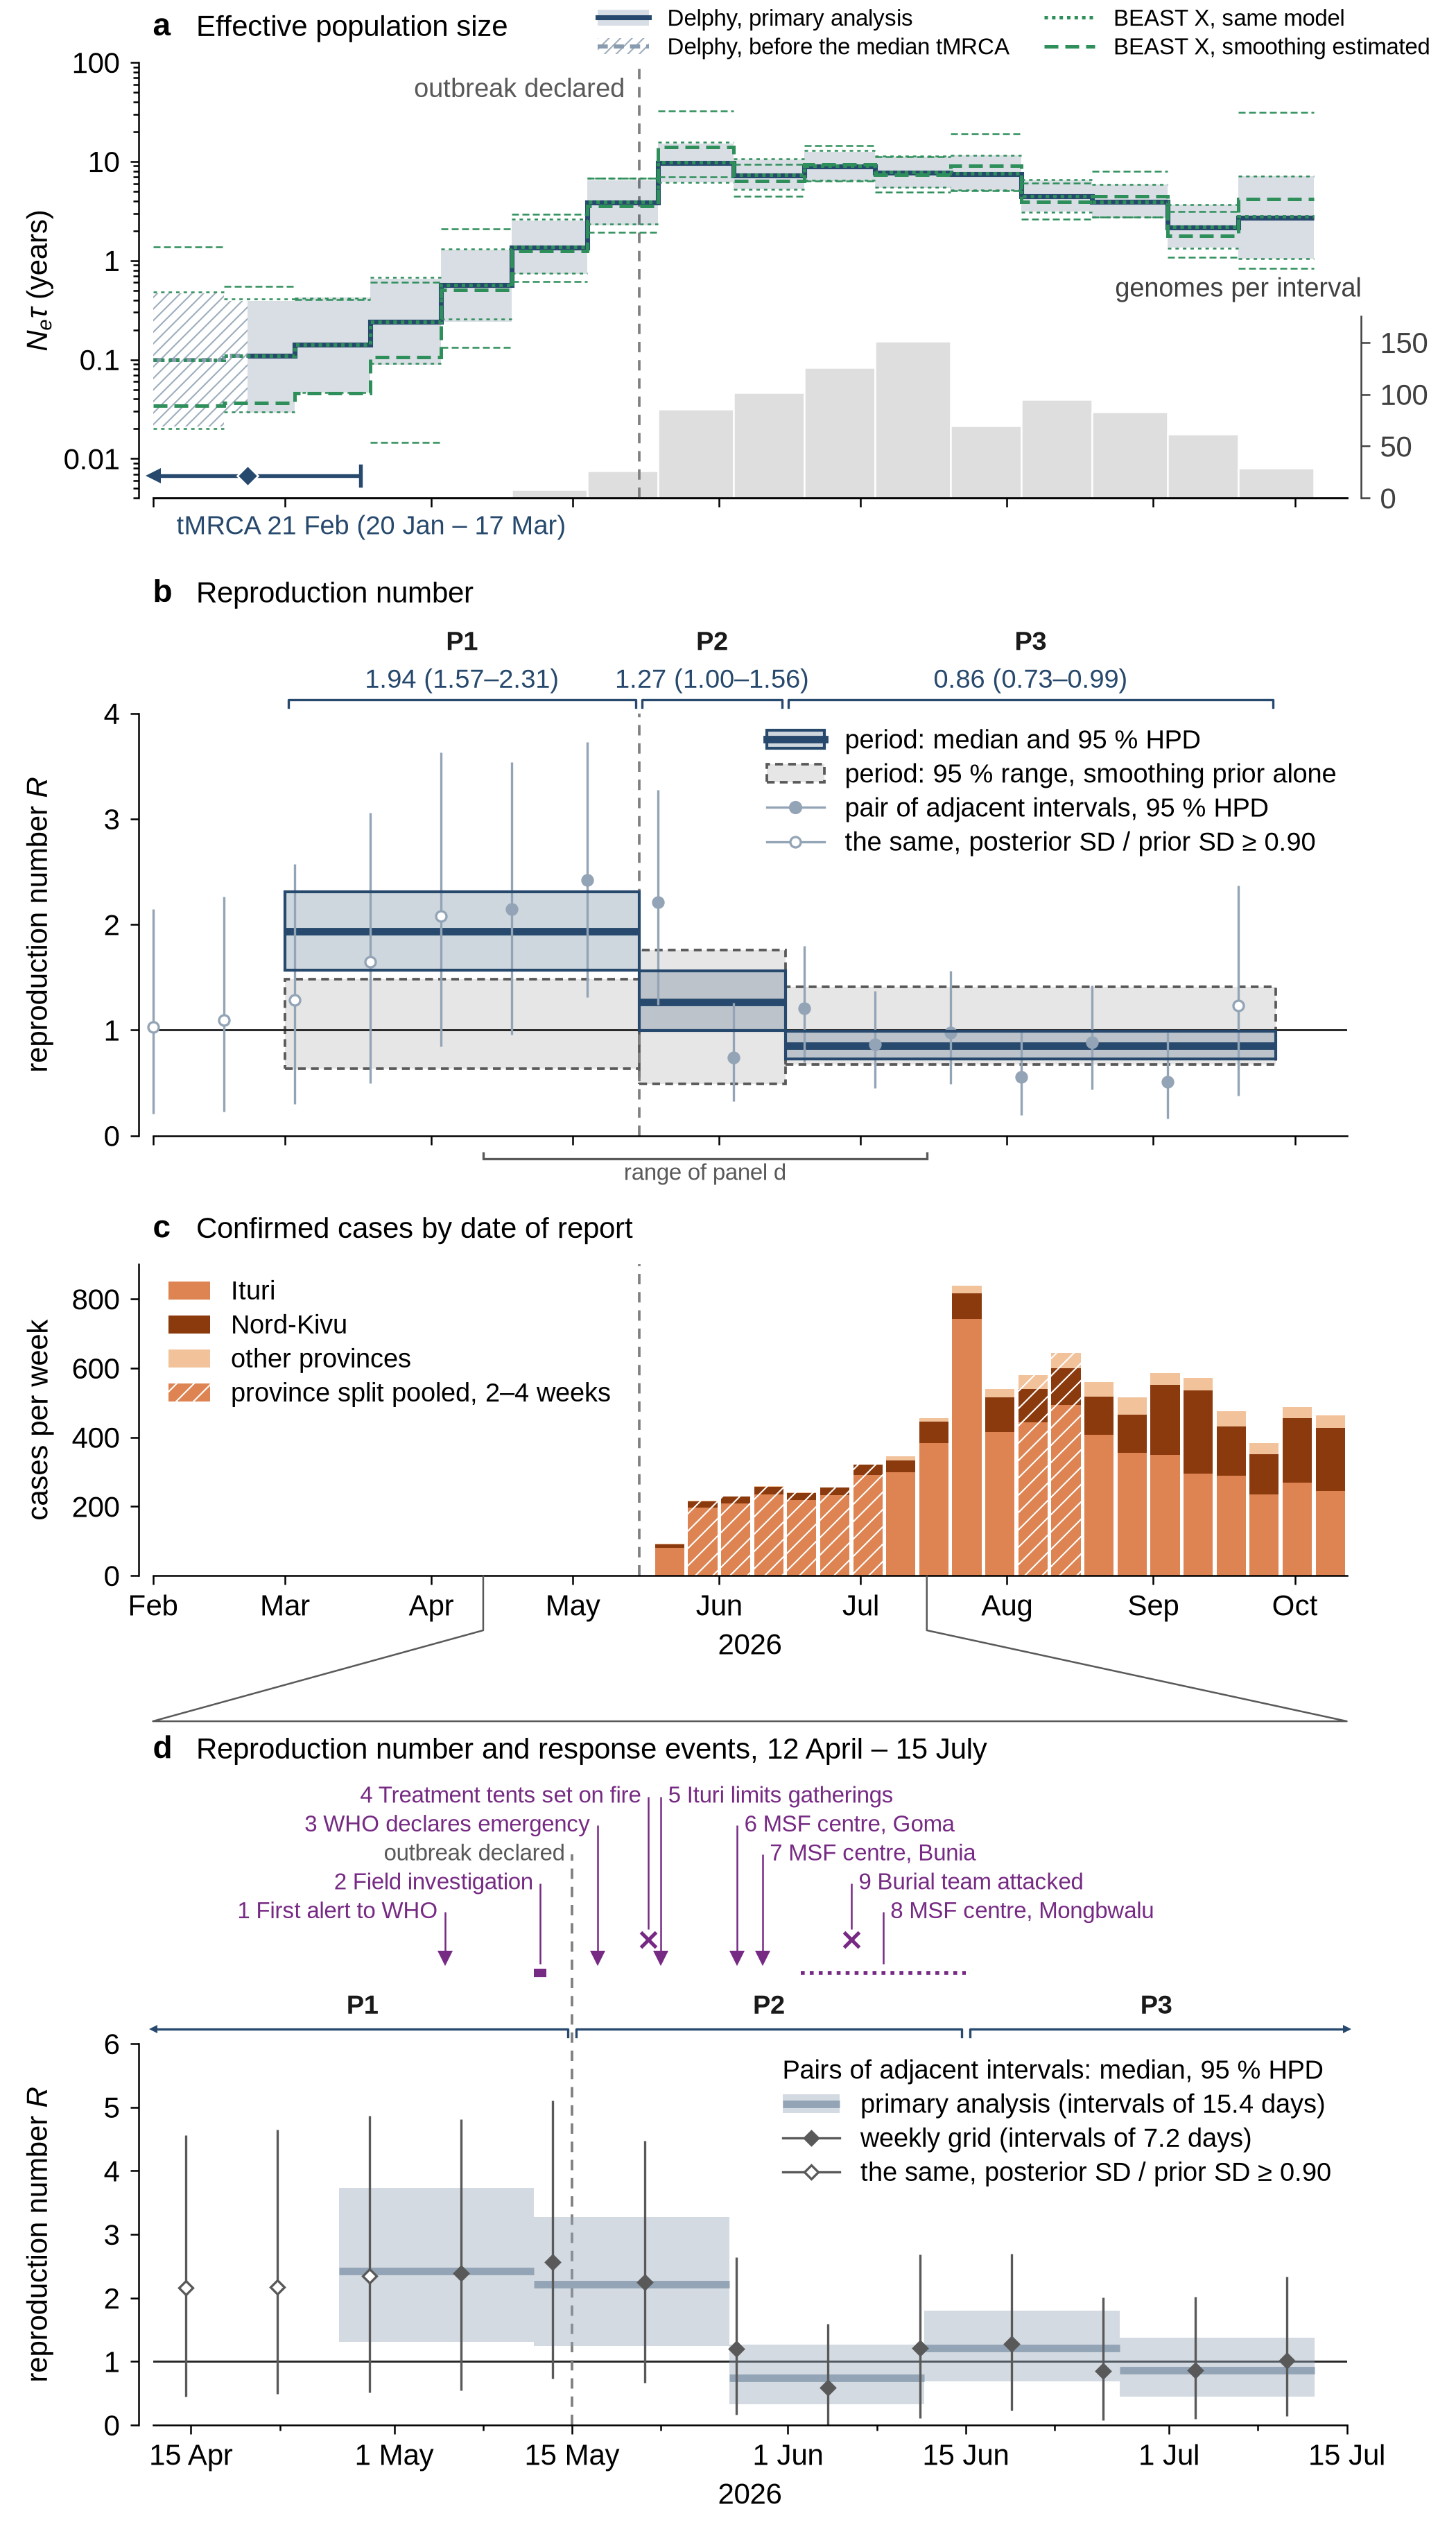
Figure 1 | Effective population size, reproduction number, and confirmed cases. a, Neτ: median and 95 % HPD interval of the primary analysis with Delphy (blue line and band; hatched: before the median Time to Most Recent Common Ancestor (tMRCA)) and of the two analyses with BEAST X (green; dotted: model of the primary analysis; dashed: smoothing estimated; thick lines: medians; thin lines: bounds of the intervals; the lower bounds of the dashed analysis in its three earliest intervals lie below the axis and are not drawn); analysed genomes per Skygrid interval (grey bars, right-hand axis). b, Reproduction number. Blue rectangles: the three periods P1 to P3 (Methods; thick line: median; height: 95 % HPD interval). Grey rectangles: 95 % range under the smoothing prior alone. Points: pairs of adjacent Skygrid intervals (median, 95 % HPD interval); open symbols: pairs with a posterior standard deviation (SD) of 0.90 or more of the prior SD, which are hardly constrained by the genomes; horizontal line: R = 1. c, Confirmed cases per week by date of report and province, from INSP situation reports N°001–150 (14 May – 11 October 2026) as transcribed in [4]; hatched: split by province pooled over several weeks. d, Reproduction number between 12 April and 15 July 2026, with the response events annotated. Bands: the five pairs of adjacent Skygrid intervals of the primary analysis with both mid-points in this range (points in b), each drawn over the time between the mid-points of its two intervals (thick line: median; height: 95 % HPD interval). Diamonds: pairs of adjacent intervals of the analysis with a weekly grid (32 parameters, intervals of 7.2 days; Methods; Figure 2), at the time at which the two intervals meet (median, 95 % HPD interval; open symbols and horizontal line as in b). The 95 % HPD interval of each of these 13 pairs includes R = 1, and their posterior SD is 0.77–0.93 of the prior SD (bands: 0.51–0.72), so changes from week to week are not resolved. Response events are shown at their dates: 1: first alert to WHO of a cluster of deaths in Mongbwalu Health Zone, 5 May [13]; 2: field investigation by the rapid response team in the health zones of Mongbwalu and Rwampara, 12 – 13 May [13, 14]; 3: WHO determines a public health emergency of international concern, 17 May [15]; 4: two treatment tents at Rwampara Hospital are set on fire, 21 May [14, 16]; 5: the military governor of Ituri bans funeral wakes, limits gatherings to 50 persons, and reserves burials to the response teams, 22 May [17, 18]; 6–8: MSF’s treatment centres open in Goma (first patients 28 May [19, 20]), Bunia (30 May [24]), and Mongbwalu (between 2 and 15 June [19, 21, 22]); 9: a safe and dignified burial team is attacked, 6 June [23].
Decline in August. R is not constant within P3: the effective population size changes little from mid-June to late July and falls from August to mid-September (Figure 1a). In the exploratory division of P3 at 1 August (Methods), R is 0.95 (0.83–1.08) before and 0.70 (0.54–0.88) after. All 19 alternative analyses in Figure 2 whose genomes run to 5 October also give a 95 % HPD interval for August below 1 (medians 0.65–0.76, upper bounds at most 0.93; data not shown). The size of the fall is less certain: R is lower in August than in the weeks before with posterior probability 0.97, by 0.25 (95 % HPD −0.01 to 0.51). Bunia supplies 148 of the 269 genomes collected since 5 August, and the model can read genomes sampled densely from one place as a small population [10, 11]; if that were producing the decline, removing Bunia genomes should raise the estimate. Without 95 of them, the P3 median is 0.81–0.86, against 0.82–0.87 in control sets with as many recent genomes removed at random; without all 148 it is 0.79, against 0.83–0.91 (Methods). The two comparisons disagree, so whether sampling in Bunia affects the decline is unclear, but neither shows a rise without Bunia genomes. As a rough check, a log-linear fit to weekly confirmed cases in the seven health zones that supply 90 % of the genomes gives R of about 0.8 for the weeks ending 9 August – 6 September, close to the August estimate and about 1.4 for the weeks ending 21 June – 2 August, above the estimate of 0.95 (0.83–1.08); a peak of reports in late July raises the second value, which is 1.2 without that week (Methods).
Unresolved rise in September. In the second half of September the median estimate lies above 1: the last point of Figure 1b, for the two most recent Skygrid intervals, is 1.23 (0.38–2.37). This apparent rise is not established: the most recent interval (19 September – 5 October) holds 29 of the 838 genomes, the posterior standard deviation of this point is 0.91 of that under the smoothing prior alone, so it is hardly constrained by the genomes (open symbol in Figure 1b), and these last weeks of the estimate can change as later genomes are added; we therefore do not extend the exploratory division beyond 1 September. By the rough comparison to case counts, cases in the seven health zones continued to fall (R of about 0.7 for the weeks ending 13 September – 11 October).
Robustness. In the 13 analyses with other genome sets, last collection dates, or grid or fixed smoothing, the median R lies between 1.76 and 2.11 for P1, between 1.22 and 1.43 for P2 and, in the seven in which P3 ends on 27 September, between 0.84 and 0.92 for P3 (Figure 2); the 95 % HPD interval for P1 lies above 1 in all of them. BEAST X gives nearly the same estimates with the model of the primary analysis: 1.94 (1.59–2.33), 1.27 (0.99–1.55), and 0.86 (0.74–1.00).
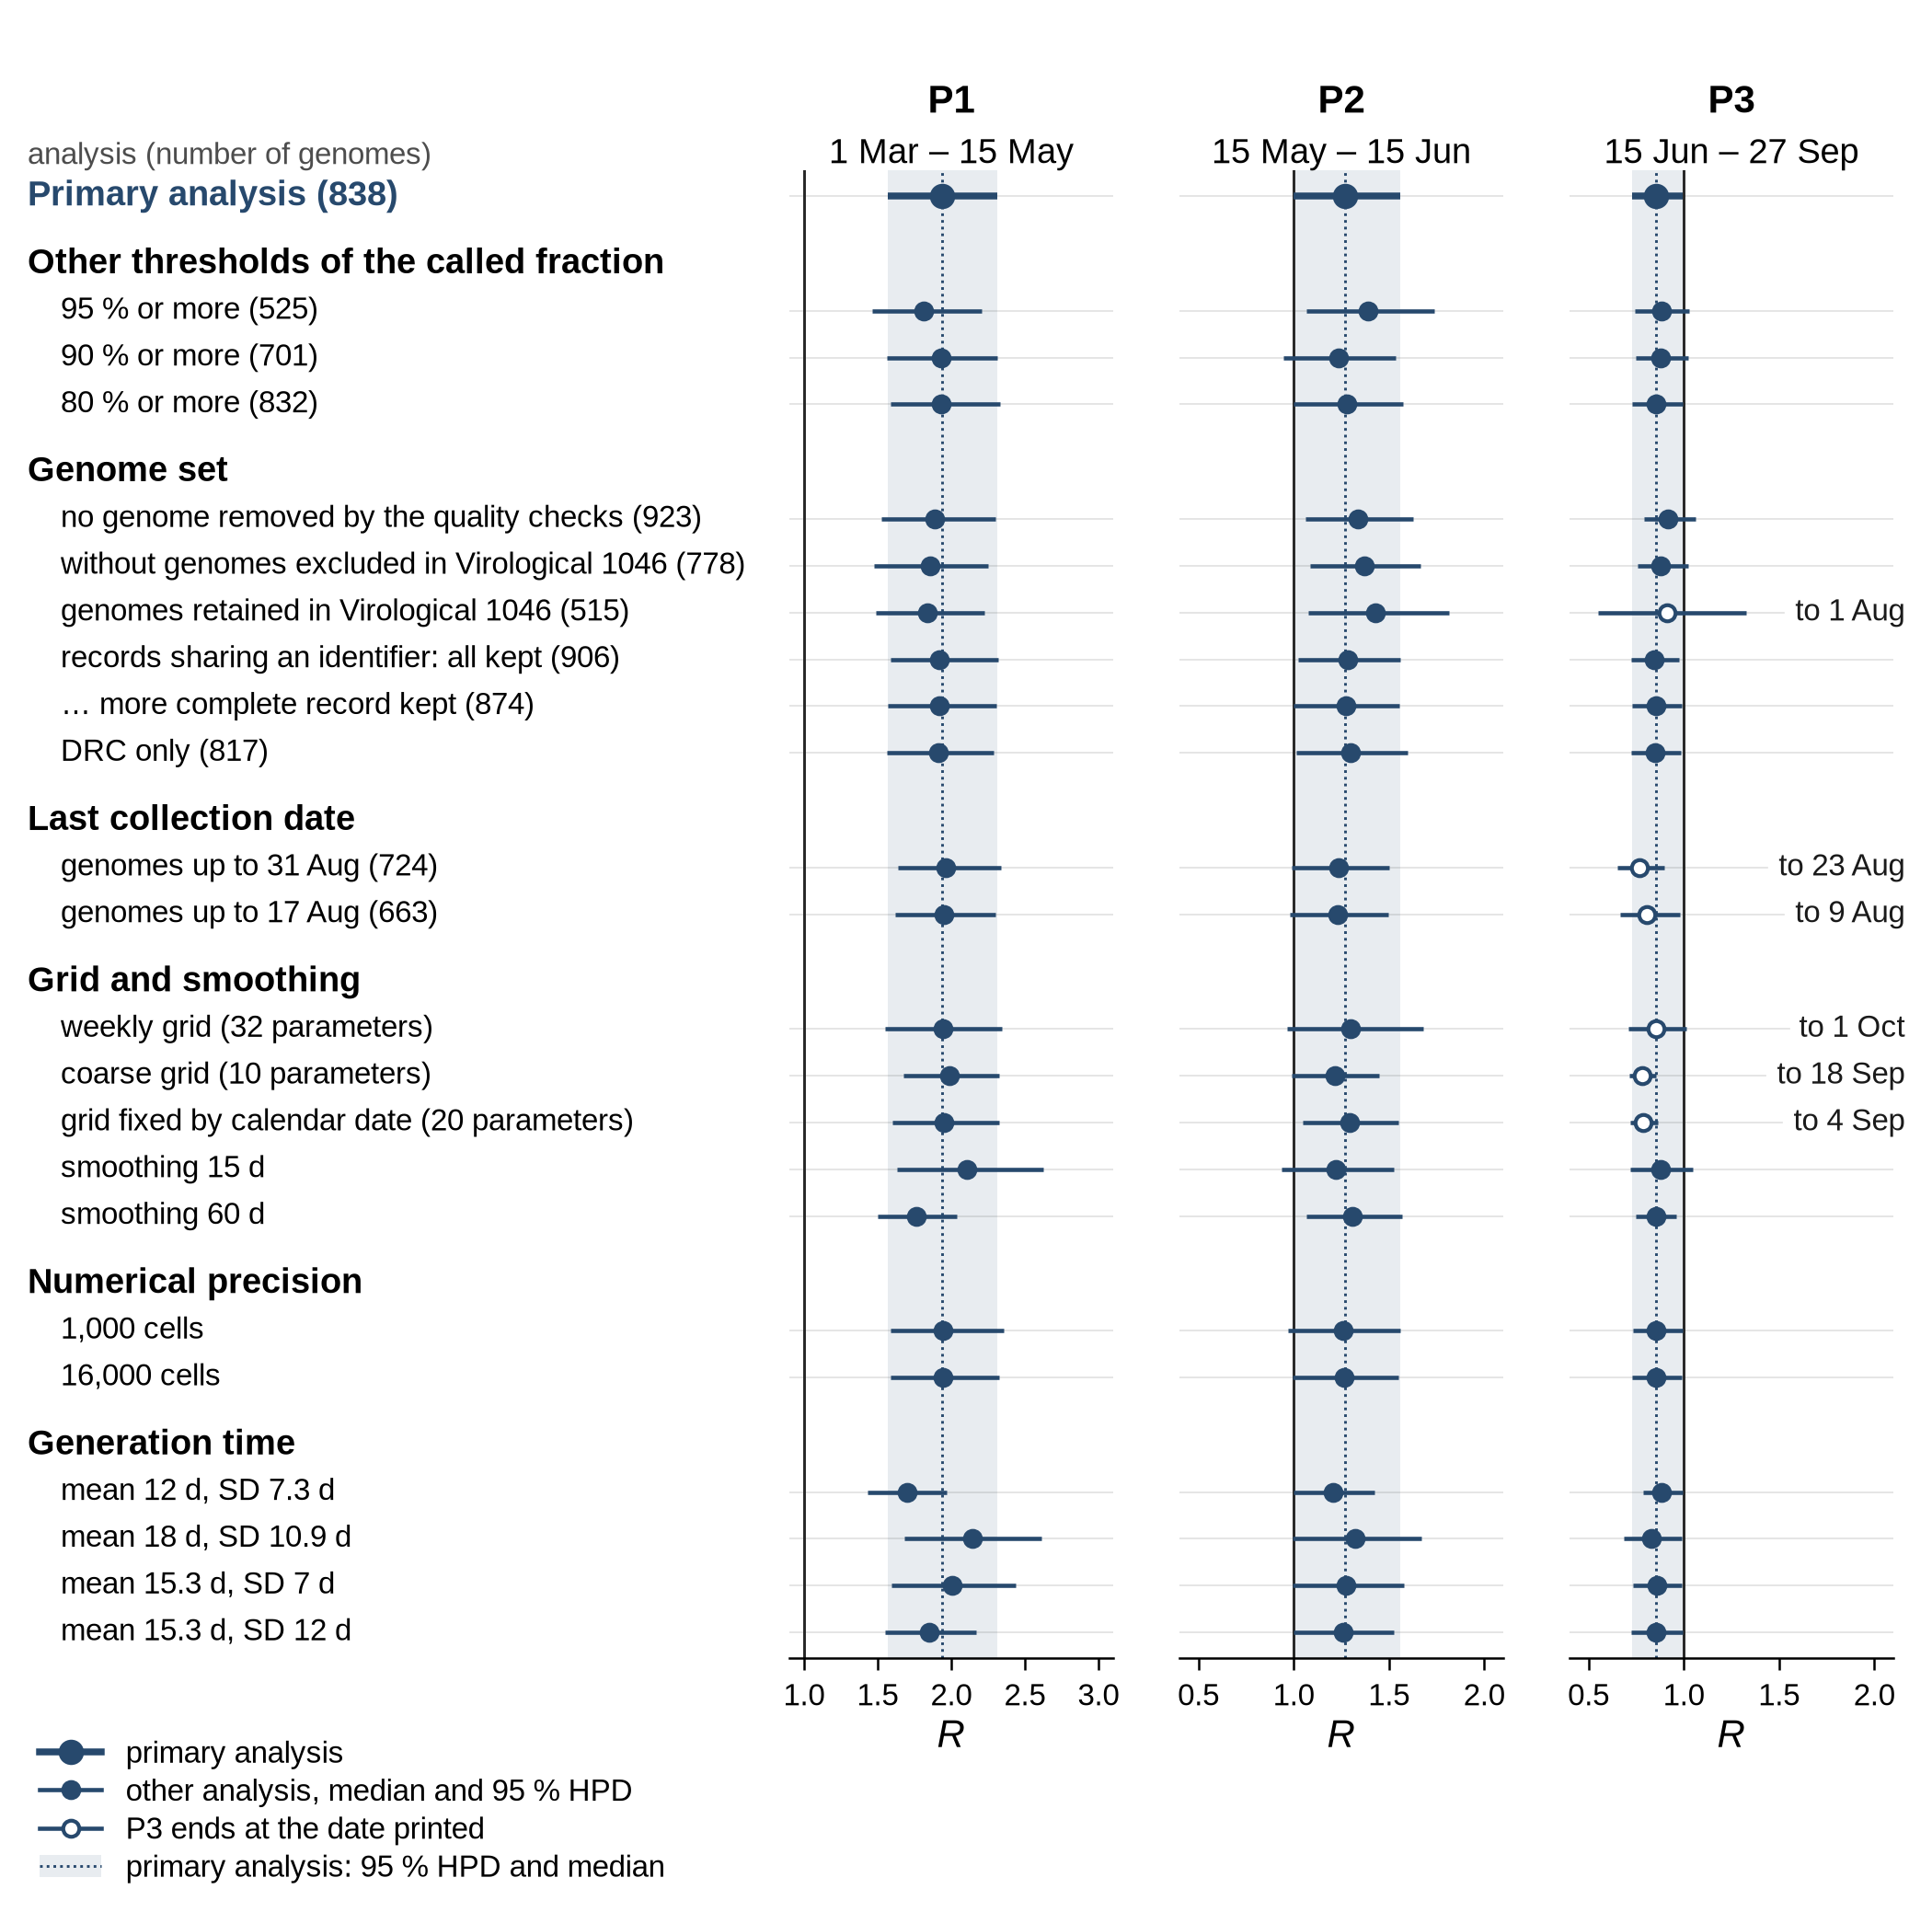
Figure 2 | Reproduction number in the three periods (P1 to P3) under other selections of genomes, settings of the model, and generation times. Symbols: posterior median; bars: 95 % HPD interval; vertical line: R = 1; band and dotted line: primary analysis (n = 838). Open symbols: the last period ends at the date printed (the most recent genome or the Skygrid intervals differ). A number alone in brackets is the number of genomes in the analysis. Other thresholds of the called fraction: the same analysis restricted to genomes with a base called at 95 %, 90 %, or 80 % or more of the 18,900 unmasked positions; the primary analysis sets no threshold. “Virological 1046” is our previous post [7], for which the genomes were selected by other criteria; one row shows the estimates for the genomes retained there, the other those for the analysed set of this post without the 60 of its genomes that were excluded there. Numerical precision: Delphy evaluates the coalescent prior on a division of time into cells; these rows change their number (primary analysis: 8,000). Smoothing: time within which the population size changes by a factor of 2 or less with a prior probability of 68 % (primary analysis: 30 days). Generation time: the posterior sample of the primary analysis converted with another generation time (primary analysis: mean 15.3 days, SD 9.3 days).
Smoothing fixed or estimated. Estimated instead of fixed, the smoothing precision is 0.90 (0.15–2.21) with Delphy and 0.81 (0.13–2.11) with BEAST X, against the fixed 4.06: on the scale used in Methods, a change by a factor of 2 within 6.6 days (1.1–16.3) and 6.0 days (1.0–15.5) instead of 30, which is short against a generation time of 15.3 days. The estimate before the official declaration, a period that mostly precedes the first genome, is then higher and less precise: 2.22 (1.55–3.00) with Delphy and 2.31 (1.56–3.47) with BEAST X. Its uncertainty probably lies between the two: the interval with the fixed default may be too narrow, that with the estimated smoothing too wide. The medians of the two later periods differ from the primary analysis by at most 0.08 (exploratory division: at most 0.06; 1.01 and 0.68 with Delphy against 0.95 and 0.70), and growth after the official declaration is slower than before with posterior probability 0.99 or more in both programs.
Interpretation and limitations. Before the official declaration, one case infected about two others on average. This estimate does not depend on the most recent genomes. Its largest uncertainties are the smoothing of the model (R = 1.76 and 2.11 where it is fixed over 60 and 15 days; 2.22 and 2.31 where it is estimated; Results), the generation time, which is the serial interval of Ebola virus disease (R = 1.70–2.14 for means of 12–18 days), and the choice of the period (Figure 1b). Growth slowed within a month after the official declaration, but these data alone cannot attribute the slowing to the response (Figure 1d). Nor do the estimates show that transmission has fallen in the outbreak as a whole: they describe the virus population sampled in Ituri; reported cases in the same health zones rose in June and July while the effective population size did not; and cases in Nord-Kivu rose until mid-September and again in the week ending 4 October (188 after 116 the week before). The analysed genomes also increasingly miss where cases are reported: the seven health zones that supply 90 % of them accounted for about 84 % of confirmed cases in the week ending 7 June but about 49 % between 5 August and 5 October, and Bunia supplied 55 % of the genomes collected since 5 August but only ~18 % of the cases. Lastly, the coalescent model assumes one well-mixed population sampled at random; its population size is constant within each 15.4-day interval, and where an interval holds few coalescences the prior holds the estimate close to its neighbours, so changes within a few weeks are not resolved.
Data availability and use
All BDBV genomes analysed here are available from Pathoplexus https://pathoplexus.org [12]. The 994 genomes used (838 in the analysed set, 156 more in the other analyses of Figure 2) are collected in the Pathoplexus SeqSet PP_SS_4720.1 (PP_SS_4720.1 | Pathoplexus) [25]. Of these, 959 were generated and submitted by INRB and its partner laboratories under the Pathoplexus ‘Restricted’ licence; 35 are open data, 14 from the same laboratories and 21 from two other groups (20 from Uganda, 1 from Germany).
The case counts are from the situation reports of the Institut National de Santé Publique (INSP) of the DRC (SitRep MVE N°001–150, 14 May – 11 October 2026), as transcribed in the public repository INRB-UMIE/BDBV2026-Data [4].
Authors
In alphabetical order; grouped by institution:
- Collins Tanui (Africa CDC)
- Justus Nsio (Africa CDC)
- Yap Boum II (Africa CDC)
- Yenew Kebede (Africa CDC)
- Laura Luebbert (Anthropic, USA)
- David Blazes (Gates Foundation)
- Sofonias Kifle Tessema (Gates Foundation)
- Adrienne Amuri-Aziza (INRB and Basic Sciences Department at the University of Kinshasa, Kinshasa DRC; Department of Clinical Sciences at the Institute of Tropical Medicine Antwerp Belgium and Department of Microbiology, Immunology and Transplantation KU Leuven, Belgium)
- Dav Ebengo (INRB, INOHA, Kinshasa, DRC)
- Emmanuel Lokilo-Lofiko (INRB, Kinshasa, DRC)
- Gradi Luakanda-Ndelemo (INRB, Kinshasa, DRC)
- Prince Akil (INRB, Kinshasa, DRC)
- Sifa Kavira (INRB, Kinshasa, DRC)
- Daniel Mukadi (INRB, University of Kinshasa, Kinshasa, DRC)
- Eddy Kinganda-Lusamaki (INRB, University of Kinshasa, Kinshasa, DRC; TransVIHMI, Université de Montpellier, INSERM, IRD, Montpellier, France)
- Pauline Muswamba (INRB, University of Kinshasa, Kinshasa, DRC)
- Placide Mbala-Kingebeni (INRB, University of Kinshasa, Kinshasa, DRC; Africa CDC)
- Steve Ahuka-Mundeke (INRB, University of Kinshasa, Kinshasa, DRC)
- Tania Bishola (INRB, University of Kinshasa, Kinshasa, DRC)
- Tony Wawina-Bokalanga (INRB, University of Kinshasa, Kinshasa, DRC; Department of Clinical Sciences, Institute of Tropical Medicine, Antwerp, Belgium)
- Dieudonne Mwamba (INSP, Kinshasa, DRC)
- Pierre Akilimali (INSP, University of Kinshasa, Kinshasa, DRC)
- Amadou Mouctar Diallo (WHO, DRC)
- Olga Ntumba (WHO, DRC)
- Nicksy Gumede (WHO Regional Office for Africa)
Acknowledgements and Funding
We gratefully acknowledge the laboratories, health authorities, and response teams that generated the genome sequences and shared them rapidly through Pathoplexus, and the teams of the Institut National de Santé Publique that compile the situation reports, and the INRB-UMIE team that transcribes them in [4]. We confirm that we have adhered to the Data Use Terms of Pathoplexus. We thank the Ministry of Public Health, Hygiene and Social Welfare of the DRC. We also thank Patrick Varilly and Andrew Rambaut for their comments and for reviewing the analyses during the preparation of this post. The authors gratefully acknowledge the ongoing support of the Africa Centers for Disease Control and Prevention (Africa CDC), the World Health Organization, and partner non-governmental organizations. We also acknowledge the support provided by the University of Manitoba (Canada), South African National Bioinformatics Institute (SANBI), Osaka Metropolitan University (OMU), Unité de Gestion du Programme de Développement du Système de Santé (UG-PDSS), the Institute of Tropical Medicine (ITM) through Belgian Directorate-general for Development Cooperation and Humanitarian Aid (DGD FA5 project), the Culmen International LLC, the US CDC Atlanta, and the Agence Française de Développement through the AFROSCREEN project (grant agreement CZZ3209), coordinated by ANRS Maladies Infectieuses émergentes in partnership with Institut Pasteur and Institut de Recherche pour le Développement, the French Ministry of Europe and Foreign Affairs through FEF programme and support provided by Institut de Recherche pour le Développement. AREBO project funded by ANRS-MIE. A.A.-A is supported by a DGD sandwich PhD scholarship. P.M-K. acknowledges the support of the Wellcome Trust through the ARTIC Network (award 313694/Z/24/Z) and the Gates Foundation. This work was supported by Anthropic, which provided the credits and compute used for the analyses. Claude Science carried out the phylodynamic runs, the estimation of reproduction numbers, and the production of figures and tables under the authors’ direction, and the analyses reported here would not have been completed in this time frame without it.
Competing Interests
L.L. is an employee of Anthropic and holds equity in the company. Anthropic develops Claude Science, the software used in this analysis. L.L. contributed to the analysis, interpretation, and writing of this post; scientific outputs were reviewed by all authors. The remaining authors declare no competing interests.
Statement on continuing work and analyses prior to publication
Please note that this data is based on work in progress and should be considered preliminary. Our analyses are ongoing, and a publication communicating our findings is in preparation. Sequences are publicly accessible under the Pathoplexus ‘Restricted’ licence and we would be grateful if the terms of this were respected. If you intend to use our data prior to our publication, please contact Dr Tony Wawina-Bokalanga (INRB, DRC) and/or Prof. Placide Mbala-Kingebeni (INRB, DRC).
References
-
de Padua B, Akhmetzhanov AR. Estimated Transmissibility and Case Fatality Rate of Bundibugyo Virus, Uganda, 2007. Emerging Infectious Diseases 2026;32. doi:10.3201/eid3210.261175
-
WHO Ebola Response Team. Ebola Virus Disease in West Africa — The First 9 Months of the Epidemic and Forward Projections. New England Journal of Medicine 2014;371:1481-1495. doi:10.1056/nejmoa1411100
-
Institut National de Recherche Biomédicale (INRB) and partners. Genomic epidemiology of the ongoing 2026 Bundibugyo Virus Disease outbreak in the Democratic Republic of the Congo. Virological.org, 9 July 2026. Genomic epidemiology of the ongoing 2026 Bundibugyo Virus Disease outbreak in the Democratic Republic of the Congo.
-
Institut National de Santé Publique (INSP), Democratic Republic of the Congo. Rapports de situation, maladie à virus Ebola (SitRep MVE), N°001–150, 14 May – 11 October 2026. https://insp.cd/ebola-17eme-epidemie/. Transcribed in: INRB-UMIE. BDBV2026-Data: data and scripts for epidemiological analysis of the 2026 Bundibugyo Ebola outbreak, folder data/insp_sitrep (state of 16 October 2026, commit 7a4d08dd). GitHub - INRB-UMIE/BDBV2026-Data: Data and scripts for epidemiological analysis of the 2026 Bundibugyo Ebola outbreak · GitHub; doi:10.5281/zenodo.20922946
-
Gill MS, Lemey P, Faria NR, et al. Improving Bayesian Population Dynamics Inference: A Coalescent-Based Model for Multiple Loci. Molecular Biology and Evolution 2013;30:713-724. doi:10.1093/molbev/mss265
-
Wallinga J, Lipsitch M. How generation intervals shape the relationship between growth rates and reproductive numbers. Proceedings of the Royal Society B: Biological Sciences 2007;274:599-604. doi:10.1098/rspb.2006.3754
-
Institut National de Recherche Biomédicale (INRB) and partners. Phylodynamics and evolution of the 2026 Bundibugyo virus circulating in the Democratic Republic of the Congo: Insights from a 100-day window of genomic sequencing. Virological.org, 25 August 2026, with the follow-up of 27 August 2026. Phylodynamics and evolution of the 2026 Bundibugyo virus circulating in the Democratic Republic of the Congo: Insights from a 100‑day window of genomic sequencing
-
Varilly P, Schifferli M, Yang K, et al. Scalable near-real-time Bayesian phylogenetics for outbreaks with Delphy. Nature 2026. doi:10.1038/s41586-026-11012-6
-
Baele G, Ji X, Hassler GW, et al. BEAST X for Bayesian phylogenetic, phylogeographic and phylodynamic inference. Nature Methods 2025;22:1653-1656. doi:10.1038/s41592-025-02751-x
-
Heller R, Chikhi L, Siegismund HR. The Confounding Effect of Population Structure on Bayesian Skyline Plot Inferences of Demographic History. PLoS ONE 2013;8:e62992. doi:10.1371/journal.pone.0062992
-
Hall MD, Woolhouse MEJ, Rambaut A. The effects of sampling strategy on the quality of reconstruction of viral population dynamics using Bayesian skyline family coalescent methods: A simulation study. Virus Evolution 2016;2. doi:10.1093/ve/vew003
-
Pathoplexus. https://pathoplexus.org; Data Use Terms: Data Use Terms | Pathoplexus
-
World Health Organization. Disease Outbreak News: Ebola disease caused by Bundibugyo virus, Democratic Republic of the Congo & Uganda (item 2026-DON602). Ebola disease caused by Bundibugyo virus, Democratic Republic of the Congo & Uganda (accessed 5 October 2026)
-
Elvis Akem T, Oben EC (2026) Operational epidemiology of the early phase of the 2026 Bundibugyo virus disease outbreak in the Democratic Republic of the Congo and Uganda. PLOS Glob Public Health 6(8): e0006680. doi:10.1371/journal.pgph.0006680
-
World Health Organization. Disease Outbreak News: Ebola disease caused by Bundibugyo virus – Democratic Republic of the Congo (item 2026-DON603). Ebola disease caused by Bundibugyo virus – Democratic Republic of the Congo (accessed 5 October 2026)
-
ALIMA. Incident at Health Facilities in Rwampara Amid the Ebola Outbreak Response - ALIMA. Press release, 21 May 2026. Incident at Health Facilities in Rwampara Amid the Ebola Outbreak Response - ALIMA (accessed 5 October 2026)
-
Radio Okapi. Ebola : interdiction des activités de masse en Ituri. 23 May 2026. Ebola : interdiction des activités de masse en Ituri | Radio Okapi (accessed 5 October 2026)
-
Agence Congolaise de Presse. Ebola en Ituri : l’exécutif provincial annonce une série de mesures pratiques à observer - ACP. 22 May 2026. https://acp.cd/nation/ebola-en-ituri-lexecutif-provincial-annonce-une-serie-de-mesures-pratiques-a-observer/ (accessed 5 October 2026)
-
Médecins Sans Frontières. DRC: One month on, MSF warns dangerous gaps persist in Ebola disease response. Press release, 15 June 2026. DRC: MSF warns dangerous gaps persist in Ebola disease response | MSF (accessed 5 October 2026)
-
Médecins Sans Frontières Luxembourg. Épidémie Ebola causée par le virus Bundibugyo — Association d’aide médicale humanitaire — Médecins Sans Frontières Luxembourg. Épidémie Ebola causée par le virus Bundibugyo — Association d'aide médicale humanitaire — Médecins Sans Frontières Luxembourg (updated 30 Sept 2026; accessed 5 October 2026)
-
Médecins Sans Frontières Southern Africa. Ebola outbreak in eastern DRC intensifies as MSF strengthens treatment and containment efforts. 1 June 2026. Ebola outbreak in eastern DRC intensifies as MSF strengthens treatment and containment efforts | MSF (accessed 6 October 2026)
-
Médecins Sans Frontières. DRC Ebola outbreak response needs urgent scale-up after two months. Press release, 15 July 2026. Ebola response needs urgent scale-up after two months | MSF (accessed 5 October 2026)
-
Zhang Y, Ren J, Ma X, He X (2026) The 2026 Bundibugyo virus disease outbreak in the Democratic Republic of the Congo: Virology, epidemiology, continental response, and research priorities. Infect Med (Beijing) 5(3): 100270. doi:10.1016/j.imj.2026.100270
-
Médecins Sans Frontières UK. In photos: Inside MSF’s Ebola Treatment Centres. 2 June 2026, updated 24 June 2026. In photos: Inside MSF's Ebola Treatment Centres | MSF UK (accessed 22 October 2026)
-
Pathoplexus. SeqSet PP_SS_4720.1. doi:10.62599/PP_SS_4720.1